
Is a Upper Respiratory Infection Contagious? (Honest Answer)
- What Is an Upper Respiratory Infection?
- Is a URI Actually Contagious?
- How Does a URI Spread?
- How Long Is a URI Contagious?
- Symptoms and Contagion Timeline
- Viral vs. Bacterial URI: Does It Change Contagiousness?
- What Most Guides Get Wrong About URI Transmission
- How to Stop Spreading a URI: Step-by-Step
- When Should You See a Doctor?
- Quick Knowledge Check
- Frequently Asked Questions
Every school year, the same cycle plays out: one student comes in sniffling on a Monday, and by Thursday half the class is reaching for tissues. Upper respiratory infections are among the most common illnesses on the planet — yet there is a surprising amount of confusion about exactly how contagious they are, when they are most dangerous to spread, and what actually works to stop them.
An upper respiratory infection (URI) is an infection of the nose, throat, sinuses, larynx, or trachea caused most often by a virus. URIs include the common cold, sinusitis, pharyngitis (sore throat), laryngitis, and similar illnesses. They are distinct from lower respiratory infections, which affect the lungs and bronchi.
In this guide, I answer the contagion question directly, correct three widely repeated myths, and give you a practical timeline so you know exactly when to stay home and when it is safe to return.
- Understand what makes a URI contagious and why
- Know the exact contagious window — including the pre-symptom phase
- Distinguish viral from bacterial URIs and why it matters
- Apply a proven 6-step plan to reduce transmission
- Recognize warning signs that need medical attention
- Yes, URIs are contagious — spread by droplets, aerosols, and surface contact.
- You can infect others 1-2 days BEFORE you feel any symptoms.
- Peak contagion is days 1-3 of active symptoms.
- About 90-95% of URIs are viral — antibiotics do nothing for them.
- Hand-washing and ventilation reduce transmission more than masks alone.
- Stay home until fever-free for 24 hours and symptoms are improving.
| Fact | Detail |
|---|---|
| Most common cause | Rhinovirus (30-50% of cases) |
| Contagious before symptoms? | Yes — 1 to 2 days before onset |
| Peak contagious window | Days 1-3 of symptoms |
| Total contagious period | Typically 7-10 days |
| Primary spread route | Respiratory droplets + hand-to-face contact |
| Viral vs. bacterial | ~90-95% viral |
| Antibiotics effective? | No (for viral URIs) |
| Vaccine available? | Only for influenza and some specific strains |
What Is an Upper Respiratory Infection?
An upper respiratory infection is any infectious illness that primarily affects the upper airways — the nose, sinuses, pharynx (throat), larynx (voice box), and trachea (windpipe). The defining feature is that the infection stays above the lungs.
Common types of URIs include:
- Common cold — the most frequent URI, usually caused by rhinovirus
- Sinusitis — infection or inflammation of the sinus cavities
- Pharyngitis — sore throat, which can be viral or bacterial (strep)
- Laryngitis — inflammation of the larynx causing hoarseness
- Epiglottitis — a rarer, more serious infection of the epiglottis
- Otitis media — middle ear infection, often a complication of a cold
URIs are not the same as lower respiratory infections like pneumonia or bronchitis, which involve the lungs and tend to be more serious.
  UPPER RESPIRATORY TRACT          LOWER RESPIRATORY TRACT
  ─────────────────────────         ─────────────────────────
  Nose / Nasal Passages             Trachea (lower portion)
  Sinuses                           Bronchi
  Pharynx (Throat)                  Bronchioles
  Larynx (Voice Box)                Alveoli (Air Sacs)
  Upper Trachea                     Lungs

  URI affects HERE ↑                Pneumonia / Bronchitis ↑

  Typical URI symptoms:             Typical LRI symptoms:
  - Runny/stuffy nose               - Persistent deep cough
  - Sore throat                     - Chest pain / tightness
  - Sneezing                        - Shortness of breath
  - Mild fever                      - High fever
  - Hoarse voice                    - Wheezing
Is a URI Actually Contagious? (The Honest Answer)
Yes — and more contagious than most people realize. The honest answer is that upper respiratory infections are among the most efficiently transmitted illnesses humans encounter, largely because they evolved to spread before the host even knows they are sick.
Here is the part that surprises most students and parents: the question is not really whether a URI is contagious, but when it is most contagious and through which routes. The answer to those questions changes your behavior in practical ways.
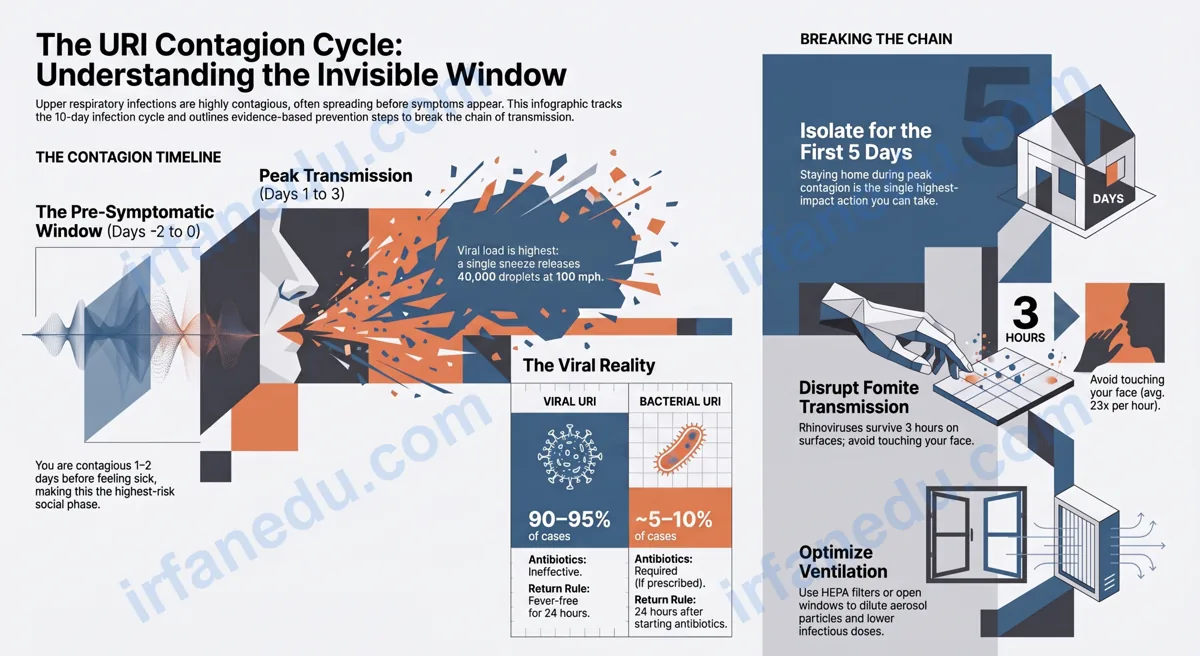
Rhinovirus — the most common URI pathogen — can survive on hard surfaces for up to 3 hours. A single sneeze releases up to 40,000 droplets at speeds approaching 100 mph. Those droplets carry viral particles that, if they land on a mucous membrane (eyes, nose, mouth), can establish a new infection with as few as 1-30 viral particles in some studies.
In my experience teaching health science to students, the biggest misconception I encounter is the belief that you are only contagious when you feel sick. This is wrong, and it is the reason URIs spread so effectively in schools and offices. The pre-symptomatic window — that 1-2 day period before you notice anything — is when you are most socially active and therefore most likely to spread the virus. Understanding this changes how you think about prevention entirely.
How Does a URI Spread?
Upper respiratory infections spread through three main routes, and knowing all three is essential for effective prevention.
Route 1: Respiratory Droplets
When an infected person coughs, sneezes, talks, or even breathes, they release droplets containing viral particles. Large droplets (greater than 5 micrometers) travel up to 3-6 feet and fall quickly due to gravity. This is the most commonly discussed route.
Route 2: Airborne (Aerosol) Transmission
Smaller aerosol particles (less than 5 micrometers) can remain suspended in the air for minutes to hours, especially in poorly ventilated indoor spaces. This route is less discussed but highly relevant in classrooms, offices, and public transport. Opening a window is not just a comfort measure — it actively dilutes viral particle concentration.
Route 3: Fomite (Surface) Contact
Viral particles land on surfaces — phones, keyboards, doorknobs, faucet handles — and survive there for minutes to hours. When you touch a contaminated surface and then touch your eyes, nose, or mouth, you self-inoculate. Studies show people touch their faces an average of 23 times per hour, which makes this route remarkably efficient.
A student with a URI arrives at school on Day 2 of pre-symptomatic infection. During a 45-minute class, they sneeze twice (uncovered), touch their desk, and share a pencil. By the end of class, rhinovirus particles are present on: the shared pencil, the desk surface, the door handle, and in the air near their seat. Three classmates who sat within 6 feet, touched the desk, or touched the pencil and then their faces are now exposed. This is not a worst-case scenario — it is a typical Tuesday.
How Long Is a URI Contagious?
A URI is contagious from approximately 1-2 days before symptoms appear until symptoms fully resolve — a total window of roughly 7-10 days for most viral URIs.
The contagious period breaks down into three phases:
- Pre-symptomatic phase (Days -2 to 0): You feel fine but are shedding virus. This is the most dangerous phase socially because you have no reason to change your behavior.
- Peak contagious phase (Days 1-3 of symptoms): Viral load is highest. Symptoms are active — runny nose, sneezing, sore throat. This is when you are most likely to spread the illness to others.
- Declining phase (Days 4-7+): Viral shedding decreases as your immune system gains control. You may still be mildly contagious, especially if symptoms persist.
What Are the Symptoms, and When Do They Make You Contagious?
URI symptoms follow a predictable progression. Knowing the timeline helps you understand when to isolate and when it is reasonable to resume normal activity.
| Day | Typical Symptoms | Contagious Level | Recommended Action |
|---|---|---|---|
| -2 to -1 | None (pre-symptomatic) | Moderate | Unknown exposure — normal hygiene |
| 1 | Scratchy throat, mild fatigue, sneezing begins | High | Stay home if possible |
| 2-3 | Runny nose, congestion, sore throat, possible low fever | Highest | Stay home |
| 4-5 | Congestion peaks, cough may develop, fatigue | Moderate | Stay home if fever present |
| 6-7 | Symptoms improving, residual cough/congestion | Low-Moderate | Return if fever-free 24 hrs |
| 8-10 | Mostly resolved; possible lingering cough | Low | Generally safe to return |
Viral vs. Bacterial URI: Does It Change Contagiousness?
Both viral and bacterial URIs are contagious, but the cause matters enormously for treatment — and slightly for transmission dynamics.
| Feature | Viral URI | Bacterial URI |
|---|---|---|
| Frequency | ~90-95% of URIs | ~5-10% of URIs |
| Common pathogens | Rhinovirus, adenovirus, coronavirus, RSV | Group A Streptococcus, Haemophilus influenzae |
| Antibiotics effective? | No | Yes (when prescribed) |
| Contagious? | Yes | Yes |
| Typical duration | 7-10 days | Varies; improves faster with antibiotics |
| Diagnosis | Clinical (symptoms) | Throat swab / rapid test (e.g., strep test) |
| Return-to-school rule | Fever-free 24 hrs + improving | 24 hrs after antibiotics started + fever-free |
The critical point: taking antibiotics for a viral URI does not shorten your illness, does not reduce contagiousness, and contributes to antibiotic resistance. According to the CDC, antibiotic-resistant infections cause more than 2.8 million illnesses annually in the United States alone. Demanding antibiotics for a cold is not just ineffective — it is actively harmful at a population level.
I have seen this pattern repeatedly: a parent brings a child with a clear viral cold to the doctor, gets told no antibiotics are needed, and then visits a second doctor hoping for a different answer. I understand the impulse — you want to do something. But the science here is unambiguous. The most effective thing you can do for a viral URI is rest, hydrate, manage symptoms, and stay home to protect others. That is not a passive response; it is the correct medical response.
What Most Guides Get Wrong About URI Transmission
Most articles about URI contagiousness repeat the same three oversimplifications. Here is where they go wrong — and what the evidence actually says.
| Common Misconception | What the Evidence Says |
|---|---|
| “You are only contagious when you have symptoms.” | False. Pre-symptomatic shedding begins 1-2 days before any symptoms appear. This is one of the primary reasons URIs spread so efficiently in schools. |
| “Cold weather causes colds.” | Cold weather does not cause URIs. Rhinoviruses replicate slightly better at cooler nasal temperatures (~33°C vs. 37°C core body temp), and people spend more time indoors in winter — increasing exposure. The virus causes the illness, not the temperature. |
| “Masks alone are sufficient prevention.” | Masks reduce droplet transmission but have limited effect on fomite transmission (surface contact). Hand hygiene and ventilation are equally or more important for URI prevention in community settings. |
The “dose-response” problem in URI transmission is almost never discussed in general health articles. Whether you get infected after exposure depends not just on whether you encountered the virus, but on the infectious dose — the number of viral particles that reach your mucous membranes. A brief handshake with someone who sneezed hours ago may deliver a sub-infectious dose; sitting next to a symptomatic person in a closed car for 30 minutes likely delivers a much higher one.
This means that reducing exposure time and improving ventilation are not just “nice to haves” — they directly reduce the probability of crossing the infectious dose threshold. Cutting your exposure in half does not halve your risk linearly; for many viruses, it reduces risk disproportionately because you stay below the threshold needed to establish infection. This is why a 10-minute outdoor conversation carries far less risk than a 10-minute indoor one, even at the same distance.
How to Stop Spreading a URI: Step-by-Step
If you have a URI, these six steps reduce the probability of infecting others. They are listed in order of evidence-based impact.
- Stay home during peak contagion (Days 1-5). This is the single highest-impact action. No other measure compensates for putting a highly contagious person in a shared space.
- Cover coughs and sneezes with your elbow, not your hand. Your elbow does not then touch shared surfaces. A tissue is also fine — dispose of it immediately and wash your hands.
- Wash hands with soap and water for 20 seconds. Do this after blowing your nose, before eating, and after touching shared surfaces. Alcohol-based hand sanitizer (at least 60% alcohol) is an effective substitute when soap is unavailable.
- Stop touching your face. This is harder than it sounds — the average person touches their face 23 times per hour. Awareness alone reduces this. Keep hands busy if needed.
- Disinfect high-touch surfaces daily. Focus on phones, keyboards, light switches, doorknobs, and faucet handles. Standard household disinfectants are effective against rhinovirus and most URI pathogens.
- Improve ventilation in shared spaces. Open windows, use exhaust fans, or use a HEPA air purifier. This reduces the concentration of airborne aerosol particles and lowers the infectious dose for others in the room.
When Should You See a Doctor for a URI?
Most URIs resolve on their own within 7-10 days and do not require medical attention. However, certain signs indicate a complication or a more serious illness that needs evaluation.
Seek medical care if you or your child experiences:
- Fever above 103°F (39.4°C) in adults, or any fever in infants under 3 months
- Symptoms that worsen significantly after day 5 instead of improving
- Difficulty breathing, shortness of breath, or chest pain
- Severe headache or stiff neck (possible meningitis — seek emergency care)
- Symptoms lasting more than 10-14 days without improvement
- Ear pain, facial pain, or pressure suggesting bacterial sinusitis or ear infection
- Rash accompanying a sore throat (possible scarlet fever — requires antibiotics)
Quick Knowledge Check
Test Your Understanding
1. When is a person with a URI typically MOST contagious?
2. About what percentage of upper respiratory infections are caused by viruses?
Sources & References
Written and fact-checked by Dr Irfan Mansuri. External links open in a new tab and are provided for further reading and verification.