
How to Use a Corrected Calcium Calculator (With Formula & Examples)
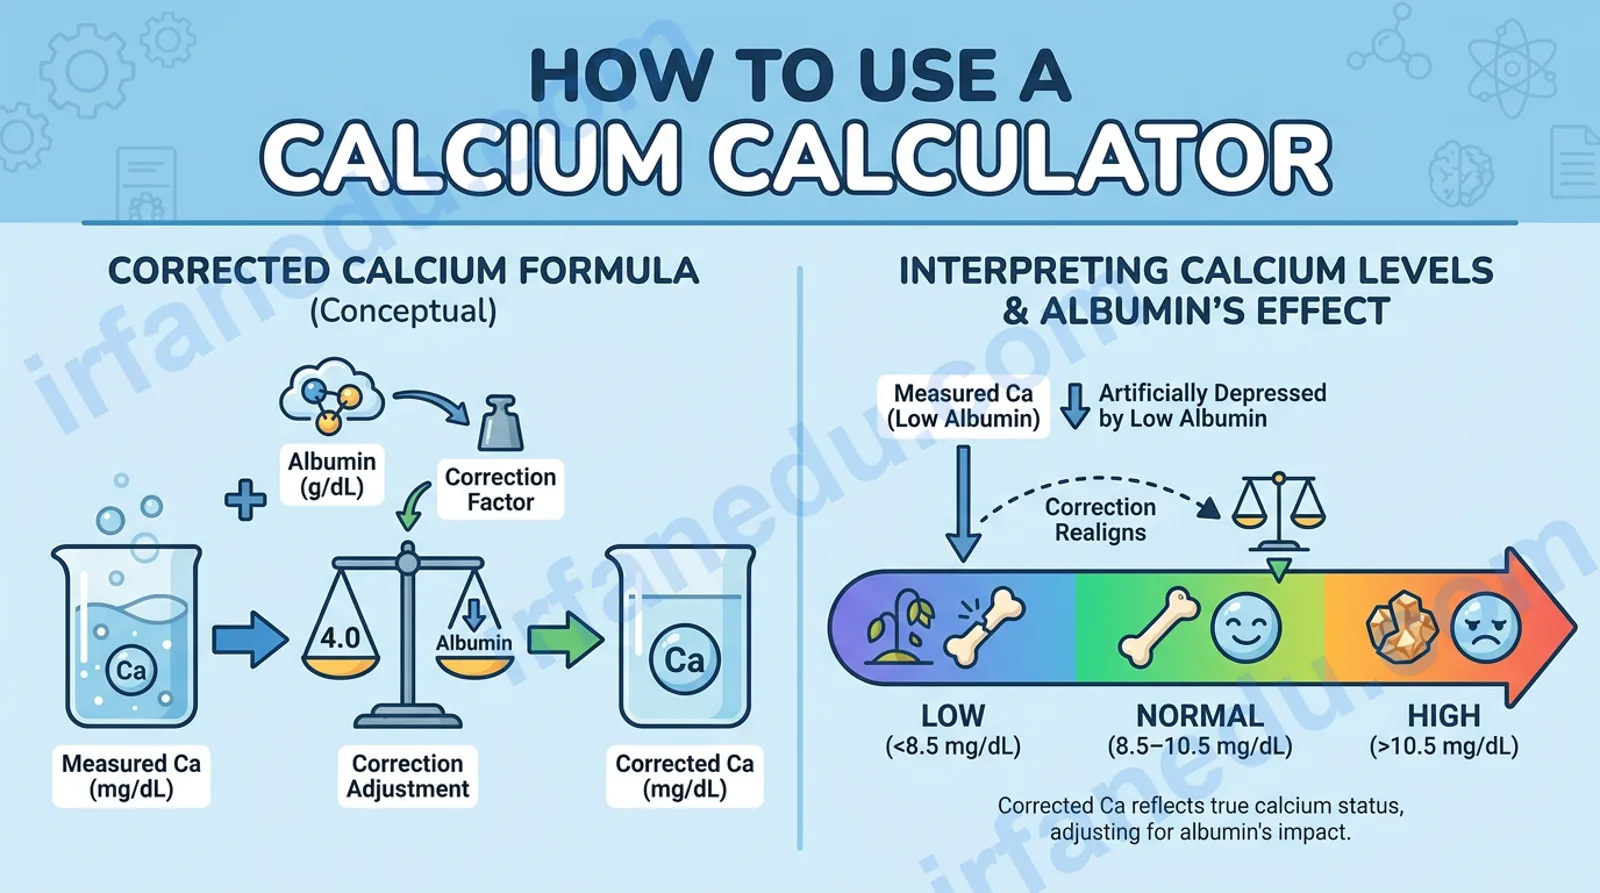
Whether you are a nursing student seeing your first hypoalbuminemia case or a pre-med reviewing electrolyte physiology, this page serves both levels. Beginners get a plain-English walkthrough of why the correction exists. Advanced learners get the formula derivation, edge-case guidance, and a comparison of corrected vs. ionized calcium. The interactive calculator below handles the arithmetic instantly.
Q: What is corrected calcium and how is it calculated?
A: Corrected calcium adjusts a raw serum calcium reading for a patient’s albumin level. The formula is: Corrected Ca (mg/dL) = Measured Ca + 0.8 × (4.0 − Albumin). A normal result is 8.5–10.5 mg/dL. Low albumin artificially depresses the reported calcium, so the correction reveals the true calcium status without a separate ionized calcium test.
⚡ TL;DR
- Raw serum calcium is unreliable when albumin is abnormal.
- Formula: Corrected Ca = Measured Ca + 0.8 × (4.0 − Albumin).
- Normal corrected calcium: 8.5–10.5 mg/dL in US labs.
- Low albumin → measured Ca is falsely low; high albumin → falsely high.
- Use ionized calcium for critically ill patients; corrected Ca is a bedside estimate.
- This calculator is for education only — not a substitute for clinical judgment.
Corrected Calcium Calculator
Payne formula — US units (mg/dL & g/dL)
mg/dL
Step-by-step solution
How to use this calculator
- Select Standard mode to find corrected calcium, or Solve for albumin needed to work backwards.
- Enter the patient’s measured serum calcium in mg/dL (from the basic metabolic panel or comprehensive metabolic panel).
- Enter the serum albumin in g/dL (from the same or a recent lab draw).
- Click Calculate (or press Enter). The result card shows the corrected value, its status (low/normal/high), an mmol/L conversion, and a numbered solution.
- Compare the corrected value to the normal range of 8.5–10.5 mg/dL.
- Bring the result to your healthcare provider. Do not act on lab values without clinical guidance.
What is corrected calcium?
Corrected calcium is a calculated estimate of what a patient’s serum calcium would be if their albumin were at the normal level of 4.0 g/dL. It matters because roughly 40–45% of total calcium in the blood is bound to albumin. When albumin drops, the measured total calcium drops with it — even if the biologically active, ionized fraction is perfectly normal.
In US clinical practice, the basic metabolic panel (BMP) and comprehensive metabolic panel (CMP) both report total serum calcium. Without an albumin correction, a patient with severe liver disease or malnutrition (both of which lower albumin) can appear hypocalcemic on paper when their ionized calcium is fine. The correction prevents unnecessary and potentially dangerous calcium supplementation.
The formula most US labs and textbooks use is the Payne formula, published in 1973 and still the standard bedside tool. According to the Wikipedia article on Calcium in biology, ionized calcium is the physiologically active fraction, but total calcium with albumin correction remains the most practical screening method in outpatient settings.
The corrected calcium formula explained
  Corrected Ca (mg/dL)  =  Measured Ca  +  0.8 × (4.0 − Albumin)
  ─────────────────────────────────────────────────────────────────
  Where:
    Measured Ca  = total serum calcium from lab report  (mg/dL)
    Albumin      = serum albumin from lab report         (g/dL)
    4.0          = normal albumin baseline               (g/dL)
    0.8          = correction factor (empirically derived)

  If Albumin < 4.0  →  (4.0 − Albumin) is POSITIVE  →  corrected Ca RISES
  If Albumin > 4.0  →  (4.0 − Albumin) is NEGATIVE  →  corrected Ca FALLS
Variables & symbols table
| Symbol | Meaning | Unit (US labs) | Typical range |
|---|---|---|---|
| Cameasured | Total serum calcium (raw lab value) | mg/dL | 7.0–12.0 mg/dL (varies with disease) |
| Albumin | Serum albumin | g/dL | 3.5–5.0 g/dL (normal adult) |
| 4.0 | Normal albumin baseline | g/dL | Fixed constant in Payne formula |
| 0.8 | Correction factor | mg/dL per g/dL | Fixed constant |
| Cacorrected | Albumin-adjusted calcium | mg/dL | 8.5–10.5 mg/dL (normal) |
SI units note: US labs report calcium in mg/dL and albumin in g/dL. To convert corrected calcium to mmol/L, divide by 4.0049. The normal range in SI units is 2.12–2.62 mmol/L.
Worked examples
Lab values: Measured Ca = 7.8 mg/dL, Albumin = 2.4 g/dL
- Albumin difference = 4.0 − 2.4 = 1.6 g/dL
- Correction = 0.8 × 1.6 = 1.28 mg/dL
- Corrected Ca = 7.8 + 1.28 = 9.08 mg/dL → Normal
Without the correction, this patient looks hypocalcemic. With it, calcium is normal. The low albumin (from, say, liver cirrhosis) was masking the true result.
Lab values: Measured Ca = 10.2 mg/dL, Albumin = 5.2 g/dL
- Albumin difference = 4.0 − 5.2 = −1.2 g/dL
- Correction = 0.8 × (−1.2) = −0.96 mg/dL
- Corrected Ca = 10.2 + (−0.96) = 9.24 mg/dL → Normal
Here, high albumin (from dehydration) inflated the raw calcium. After correction, it is normal. This is the less-taught direction of the formula.
Lab values: Measured Ca = 11.4 mg/dL, Albumin = 3.8 g/dL
- Albumin difference = 4.0 − 3.8 = 0.2 g/dL
- Correction = 0.8 × 0.2 = 0.16 mg/dL
- Corrected Ca = 11.4 + 0.16 = 11.56 mg/dL → High
Even with near-normal albumin, the corrected calcium is clearly elevated. This warrants investigation for hyperparathyroidism, malignancy, or other causes.
Corrected calcium vs. ionized calcium: when to use each
Both methods aim to assess the physiologically active calcium fraction, but they differ in accuracy, cost, and clinical setting. Here is how they compare:
| Feature | Corrected calcium | Ionized calcium |
|---|---|---|
| Method | Calculated from total Ca + albumin | Directly measured (blood gas analyzer) |
| Accuracy | Estimate; ±0.5 mg/dL error common | Gold standard |
| Cost | No extra test (uses existing BMP/CMP) | Requires separate specimen/analyzer |
| Best for | Outpatient screening, stable patients | ICU, acid-base disorders, critical illness |
| Limitations | Unreliable in myeloma, liver failure | Affected by pH; must be processed quickly |
| US normal range | 8.5–10.5 mg/dL | 4.6–5.3 mg/dL (1.15–1.33 mmol/L) |
In my experience teaching pre-med and nursing students, the most common error is treating the corrected calcium formula as infallible. It is a screening estimate, not a diagnosis. I always tell students: if the corrected calcium and the clinical picture disagree, order the ionized calcium. The formula was derived from a 1973 study of 202 patients — it is a useful heuristic, not a law of physics. Knowing its limits is what separates a good clinician from one who blindly trusts a number.
Common mistakes when using the corrected calcium formula
| Mistake | What goes wrong | Correct approach |
|---|---|---|
| Using albumin from a different day | Albumin fluctuates; stale values give wrong correction | Use albumin drawn at the same time as calcium |
| Applying the formula in multiple myeloma | Paraproteins bind calcium; formula overestimates corrected Ca | Order ionized calcium directly |
| Forgetting the formula works both ways | Students only think of low albumin; high albumin inflates raw Ca too | Always check: is albumin above or below 4.0? |
| Using mmol/L inputs with mg/dL constants | The 0.8 factor is calibrated for mg/dL Ca and g/dL albumin | Convert to US units before calculating |
| Treating corrected Ca as a diagnosis | A high corrected Ca needs a cause (PTH, PTHrP, vitamin D, etc.) | Use the result to guide further workup, not to conclude |
Important: The FDA and US clinical guidelines (including those from the American Association for Clinical Chemistry) recommend confirming borderline or unexpected corrected calcium results with a direct ionized calcium measurement before making treatment decisions.
Every guide explains the Payne formula. Almost none explain why the correction factor is 0.8 and not 1.0. Here is the non-obvious part: not all albumin-bound calcium is equally exchangeable. The 0.8 factor is an empirical average from a regression analysis of a specific patient population. In patients with abnormal albumin structure (such as in chronic liver disease where albumin is glycosylated differently), the binding affinity per gram of albumin is altered — so the true correction factor for that individual may be closer to 0.7 or even 0.6. This is precisely why the formula breaks down in advanced cirrhosis and why several nephrology textbooks now recommend skipping corrected calcium entirely in that population and going straight to ionized calcium. The formula is not wrong; it is a population average being applied to an individual, and that gap matters clinically.
Quick knowledge check
1. A patient has measured Ca = 8.0 mg/dL and albumin = 2.0 g/dL. What is the corrected calcium?
2. Which patient population makes the corrected calcium formula LEAST reliable?
3. If albumin is ABOVE 4.0 g/dL, the corrected calcium will be _____ the measured calcium.